The Thyroid Connection Nobody Mentions: How Your Thyroid Shapes Testosterone, Energy, and Drive
A man in his early forties notices that something has shifted. He sleeps seven or eight hours and wakes up flat. His training is consistent, but his midsection is growing and his recovery is slower. His drive, in the gym and in the bedroom, is lower than it was three years ago. Focus at work takes more effort than it used to.
He does what a high-performing man does with a problem. He researches it. And almost every road he takes ends at the same word: testosterone.
Testosterone may well be part of his story. But a second system produces nearly the same picture, interacts directly with testosterone, and rarely comes up in men’s health conversations at all. That system is the thyroid, and the marker that screens it is TSH.
WHAT THE THYROID ACTUALLY DOES
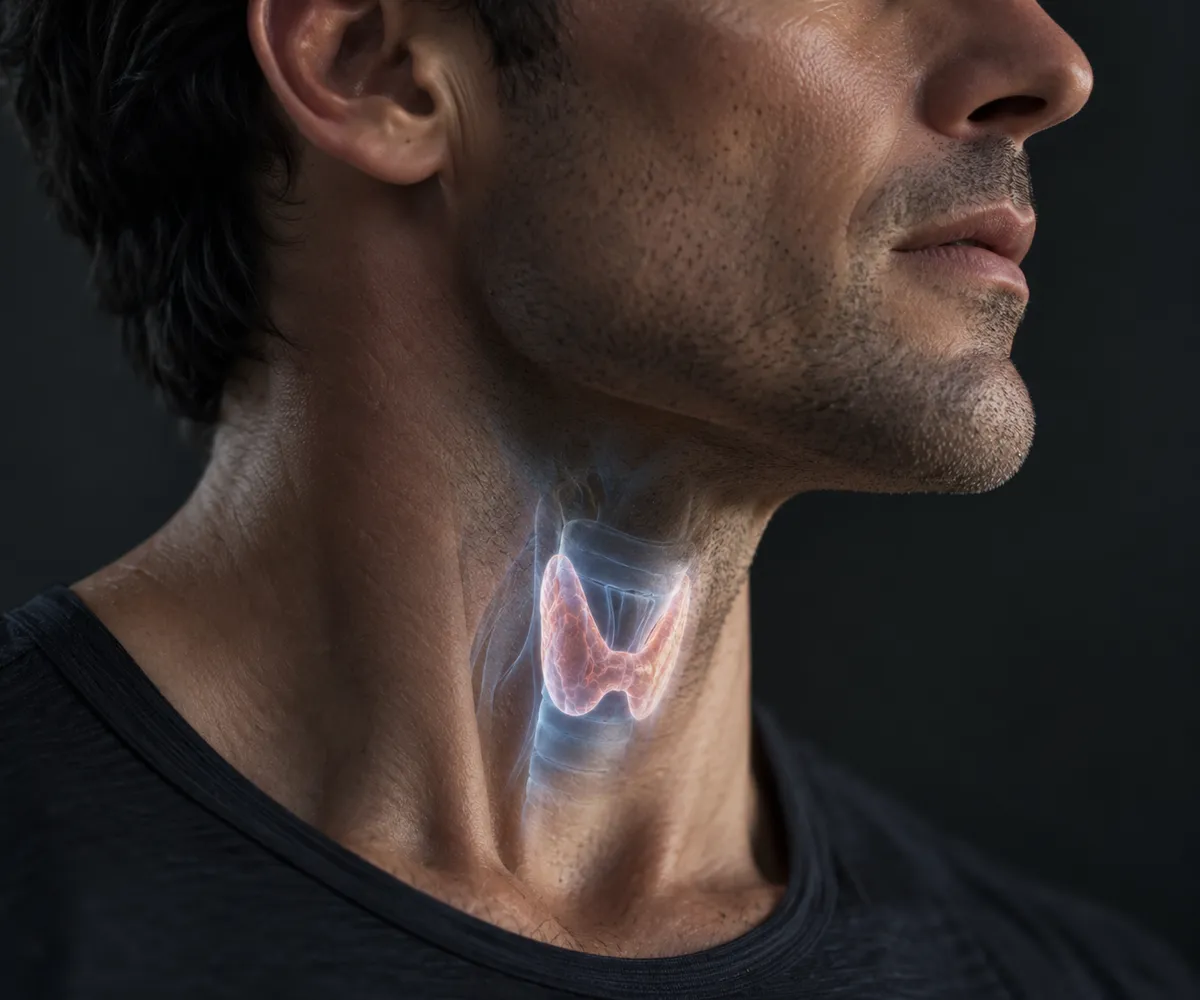
The thyroid is a small gland at the front of the neck, just below the larynx. Its hormones, primarily thyroxine (T4) and the more active triiodothyronine (T3), set the metabolic pace of nearly every tissue in the body.
That reach is the reason thyroid changes are so easy to misattribute. Thyroid hormone influences how quickly cells convert fuel into energy, how warm the body runs, how fast the heart beats, how efficiently the liver clears cholesterol, how quickly the brain processes information, and how well muscle recovers. When output drops, no single system fails dramatically. Everything slows down a little, all at once.
HOW TSH WORKS
The thyroid does not regulate itself. It takes direction from the pituitary gland, which monitors circulating thyroid hormone and adjusts its output of thyroid-stimulating hormone, TSH, in response.
The relationship is inverse. When thyroid hormone runs low, the pituitary releases more TSH to push the thyroid harder. When thyroid hormone runs high, TSH falls. A TSH reading above the expected range usually points toward an underactive thyroid. A reading below it points toward an overactive one.
Because the pituitary responds to small changes in thyroid output, TSH often moves before thyroid hormone levels themselves fall outside their range. That sensitivity is what makes it a useful screening marker.
WHAT AN UNDERACTIVE THYROID LOOKS LIKE IN MEN
The common signals of an underactive thyroid, known clinically as hypothyroidism, include persistent fatigue that sleep does not resolve, reduced sex drive, weight gain or stalled fat loss despite consistent training and eating, slower thinking often described as brain fog, lower mood and motivation, slower recovery between sessions, feeling cold more easily than others, and dry skin.
Now compare that to what men associate with low testosterone: fatigue, low libido, body composition changes, reduced focus, flat mood, slower recovery. Six of the first six items match.

WHY THYROID ISSUES GO UNNOTICED IN MEN
Thyroid problems are considerably more common in women, and that shapes who gets screened. Many men go years without a TSH check because no one thought to order one.
Thyroid underactivity also becomes more common with age. It tends to emerge in the same decade when men begin noticing changes and attributing them to testosterone, stress, or simply getting older.
There is also a milder form, subclinical hypothyroidism, in which TSH is elevated while thyroid hormone levels remain within range. It develops gradually, and its effects can be subtle enough that a man adjusts to them rather than questioning them.
Gradual change is the hardest kind to notice. A man who loses a few percent of his energy each year never experiences a moment of failure. He experiences a slow redefinition of normal.
THE PHYSIOLOGICAL LINKS BETWEEN THYROID AND TESTOSTERONE
The overlap is not just a matter of similar complaints. The two systems interact through several measurable pathways.
SHBG. Sex hormone-binding globulin is the protein that carries testosterone through the bloodstream. Thyroid hormone influences how much SHBG the liver produces. An underactive thyroid tends to lower SHBG, which can pull a total testosterone reading down. A man looking at a low total testosterone number in isolation has no way to know the thyroid is shaping it.
Prolactin. The hypothalamic signal that tells the pituitary to stimulate the thyroid, thyrotropin-releasing hormone, also stimulates prolactin. When the thyroid is underactive, that signal rises, and prolactin can rise with it. Elevated prolactin suppresses the chain of signals that tells the testes to produce testosterone. Through this pathway, a thyroid problem can produce a real reduction in testosterone.
Cholesterol. Thyroid hormone drives the liver’s clearance of LDL cholesterol. An underactive thyroid frequently raises LDL. A man who sees his cholesterol climbing may blame his diet when the thyroid is a contributor.
Erection quality. A 2008 study published in the Journal of Clinical Endocrinology & Metabolism by Krassas and colleagues compared sexual function in men with thyroid dysfunction against matched controls. Reduced erectile function was substantially more common in the men with thyroid dysfunction, and it improved markedly within a year of restoring normal thyroid function. The authors recommended screening the thyroid before starting therapy aimed specifically at erectile function, since the thyroid itself may be the primary driver.
THE OVERACTIVE DIRECTION
The thyroid can also run too fast. An overactive thyroid tends to raise SHBG, which binds more testosterone and can reduce the free fraction available to tissues even when total testosterone looks adequate. Men with an overactive thyroid can also experience lower libido and changes in sexual function. This is less common than underactivity, but it reinforces the larger point: thyroid status changes how a testosterone number should be read, in either direction.
ADDRESSING THE WRONG SYSTEM
When the thyroid is driving a man’s picture and testosterone is addressed instead, the result is often partial. Testosterone therapy raises the downstream number. The upstream cause stays in place.
Partial improvement can be worse than none, because it makes the misread harder to spot. Energy lifts a little. Drive returns partway. The weight does not move as expected, and the brain fog lingers. A man in this position often concludes that testosterone did not work for him, or that he needs a higher dose, when the real variable was never measured.
The issue is not testosterone therapy itself. Properly indicated and monitored, it is effective. The issue is sequence. Information has to come before intervention.
THE LIMITS OF A SINGLE-MARKER TEST
Much of the current men’s health market runs on a simple model: measure testosterone, and if it is low, prescribe. A single-marker test can answer one question, whether that number is low. It cannot answer the more important one, why.
It cannot see a thyroid lowering SHBG. It cannot see prolactin climbing. It cannot see the lipid shift that often travels with a slow thyroid. Every one of those findings changes what a low testosterone number means and what should happen next.
WHAT TSH CAN AND CANNOT TELL YOU
TSH is a screening marker, not a complete thyroid evaluation. A TSH within the expected range makes a significant thyroid problem much less likely. A TSH outside that range is a flag, and it typically leads to additional testing, such as free T4 and in some cases thyroid antibodies, before any conclusion is drawn.
That is the right role for a screen. It sits at the starting line, read alongside every other marker, so that if the thyroid is involved it is identified before decisions are made rather than after months of frustration.
HOW THE FULL PANEL READS TOGETHER
The Springhouse Men’s Panel includes TSH alongside free and total testosterone with SHBG, estradiol (LCMS), FSH and LH, prolactin, PSA, CBC, CMP, a lipid panel, and hemoglobin A1C.
The value is in how those markers read against one another. A low testosterone result with a normal TSH, normal prolactin, and elevated LH points in one direction. A low testosterone result with an elevated TSH, a raised prolactin, and a climbing LDL points somewhere else entirely. The same testosterone number can lead to two completely different plans depending on what sits around it.
That is why TSH belongs on a men’s panel, even though it rarely makes the conversation.
THE TAKEAWAY

If you measure your training, your sleep, and your nutrition, hold your hormones to the same standard. Testosterone is one input in an interconnected system, and the thyroid is one of the most influential and least discussed parts of it.
Before concluding that testosterone is the answer, confirm that it is the question.
At Springhouse, a consultation begins with a $100 deposit that is applied toward your services. If you move forward with the Springhouse Men’s Panel, that deposit reduces the $249 panel to $149 at the time of service.
Springhouse Men's Wellness is a physician-founded practice led by Dr. Melissa Lee-Agawa, delivered in partnership with Grace & Glow MD. These articles are written by Taka Agawa, founder, with Dr. Lee-Agawa's clinical guidance throughout. Spring House, Pennsylvania. www.springhousemen.com
